Gail Hart’s Research updates for midwives 2012 also features an interesting chapter on routines, where she asks right at the beginning – “Why do we do what we do?”
Some modern birthing practices are based on routines rather than observation and research. We do some things the same way every time just because that’s how we’ve always done them. So we do these things routinely, but we can’t explain why. To make our work the best it can be, we need to start “routinely studying our routines” to make sure they are beneficial, effective, and safe.
A “routine birth” usually means a birth taking place in a loud, bright, small space – a delivery room. Routinely, the newborn’s airways are suctioned immediately after birth, the umbilical cord is cut before it stops pulsing, there is no skin-to-skin contact or sacred hour, the newborn is washed with shampoo and/or oiled and dressed…
The transition after birth, the move to extrauterine life – is a PROCESS
After birth, mother and baby form a “unit.” For emotional and physiological reasons, we must give them enough time to adjust when they need to be separated. After long months in the womb, where everything was fully provided through the placenta and there was no need to breathe with their own lungs, etc., the baby is forced into major changes after birth. When the placental supply is cut off, the heart redirects a much larger portion of blood to the lungs and kidneys. A baby’s lungs are initially filled with fluid, but within a minute of birth, the fluid is squeezed out of the lungs into the circulatory system, and the lungs are almost clear and can fill with air. This complex process isn’t instantaneous. The transition to life outside the womb takes time for the baby to fully adapt to extrauterine life. We can influence this process.

“Fresh (oxygenated) blood flows from the placenta through the umbilical vein to the fetus. This is the only blood in the fetus that is NOT mixed. Part of this blood flows directly into the inferior vena cava and mixes with the spent (deoxygenated) blood that has flowed from the lower part of the fetal body. Another, smaller part of this oxygenated blood flows from the umbilical vein into the liver and from there through the hepatic veins into the inferior vena cava. Both the superior and inferior vena cava flow into the right atrium. A smaller part of the blood flows from there through the tricuspid valve into the right ventricle. The rest of the blood from the right atrium flows through the foramen ovale into the left atrium and then through the mitral valve into the left ventricle. The blood in the right ventricle is also divided. Part of the blood flows through the pulmonary valves into the lungs. The remaining larger amount of blood flows through the ductus arteriosus, which connects the pulmonary artery and the aorta, into the descending aorta and the lower part of the body. The blood that has flowed into the left atrium flows through the mitral valve into the left ventricle and from there into the ascending aorta, which supplies the head and the upper part of the body. Once the blood is used here, part of it returns to the vena cava and back to the heart. The rest of the blood flows through the abdominal arteries into the umbilical artery and back to the placenta, where it releases carbon dioxide and other metabolic waste products.” Source and more
How a healthy newborn “behaves” in the first half hour after birth: the newborn is active, their heart beats fast, they may have some trouble breathing, they have amniotic fluid in their mouth, body temperature drops slightly, they change color—they might be bluish at first, then turn pink…
Gail highlights some routines with which we (un)knowingly influence the newborn’s adaptation
- Routine stimulation of the newborn – gentleness is key
We must handle a newborn gently to help them better adapt to life outside the womb. Rough handling and quick movements “shock” the newborn and can make them cry before all the fluid is squeezed out of the lungs. Stimulating crying before the physiological “squeeze” of the lungs can cause uneven filling of the lungs, which can lead to respiratory distress or transient tachypnea.
After birth, place the newborn in the mother’s arms and observe them to avoid unnecessary stimulation. The newborn shouldn’t be touched, manipulated, tickled, or rubbed; they should just be in the mother’s arms and, if anything, the mother should be the one to stimulate them if she wishes. Ideally, the room should have dimmed lights, and everyone present should try to speak softly so the newborn can only hear the voices of the mother, father, and/or other family members.

Dry towels or diapers should be gently placed over the newborn and mother to absorb moisture. Rubbing the newborn to dry them isn’t necessary. If we place the baby in direct skin-to-skin contact, there’s no need to dry them beforehand at all.
A healthy newborn will “clear” their lungs and take a breath within 30 seconds. They might also cry in the first minute. Some won’t cry even if their breathing is perfectly fine, so there’s no real need for them to cry.
If the umbilical cord hasn’t been cut yet, the baby can safely transition to lung breathing over several minutes. A newborn is normally bluish after birth, but their color quickly improves to pink. It starts on the chest; hands and feet can stay bluish for up to a few days. The newborn must have normal muscle tone, irritability, color, heart rate, and breathing throughout this time (Apgar score). They need to respond to their surroundings and learn to breathe with their lungs.
If the baby is limp and pale or shows any signs of asphyxia, they need help! Such a child might need their airways suctioned, breathing stimulated, or resuscitation. Otherwise, the baby needs a gentle transition to extrauterine life.
2. Airway suctioning when the head is born
This became routine somewhere in the mid-1970s to prevent amniotic fluid aspiration in all births. At home, in hospitals, in birthing centers. This teaching was based on the theory that every newborn must be suctioned before the first breath to prevent choking on mucus or the aspiration of meconium-stained amniotic fluid into the lungs. By doing this for every newborn, we would reduce respiratory distress syndrome (RDS) and meconium aspiration syndrome (MAS).

A few years of practice showed that the percentage of meconium aspiration didn’t decrease despite the routine suctioning of all newborns. Researchers in the early 80s questioned this method, but it was already deeply embedded in the routine of birthing practices.
A large multicenter prospective, randomized controlled trial involving 2,094 babies born with meconium-stained amniotic fluid showed no reduction in the incidence of MAS after airway suctioning as soon as the head was born compared to no suctioning. (Lancet. 2004 Aug 14-20; 364 (9434):597-602; Oropharyngeal and nasopharyngeal suctioning of meconium-stained neonates before delivery of their shoulders: multicentre, randomised controlled trial Vain NE, Szyld EG, Prudent LM, Wiswell TE, Aguilar AM, Vivas NI. Sanatorio de la Trinidad Hospitals, Buenos Aires, Argentina. vain@fibertel.com.ar PMID: 15313360).
In fact, it was proven that routine suctioning of the mouth and nose is not only useless but harmful, as routine suctioning in newborns with clear fluid, after vaginal birth or C-section, is associated with bradycardia, apnea, and a delay in reaching normal saturation levels. In vigorous newborns born with meconium-stained fluid, suctioning does not prevent MAS. Depressed newborns born with meconium-stained fluid have an increased risk of aspiration. However, there is no evidence that suctioning reduces MAS (Velaphi S, Vidyasagar D.(2008 Dec) The pros and cons of suctioning at the perineum (intrapartum) and post-delivery with and without meconium. Semin Fetal Neonatal Med. 2008 Dec;13(6):375-82 also see Epub 2008 May 13.http://emedicine.medscape.com/article/1413467-overview)
A Cochrane review also shows no difference in the incidence of MAS between vigorous newborns who were suctioned and those who were not. (Cochrane review Endotracheal intubation at birth for preventing morbidity and mortality in vigorous, meconium- stained infants born at term Henry L Halliday, David G Sweet January 2009). Namely, meconium aspiration occurs in the womb, as it is a result of hypoxia already in the womb and not during the first breath. (Velaphi S, Vidyasagar D. Intrapartum and postdelivery management of infants born to mothers with meconium-stained amniotic fluid: evidence-based recommendations. Clin Perinatol. Mar 2006;33(1):29-42, v-vi.) ACOG thus advises against routine suctioning, except in the case of newborns who require resuscitation. (Obstet Gynecol. 2007 Sep;110(3):739.ACOG Committee Opinion No. 379: Management of delivery of a newborn with meconium-stained amniotic fluid. Committee on Obstetric Practice, American College of Obstetricians and Gynecologists. If meconium is present and the newborn is depressed, the clinician should intubate the trachea and suction meconium and other aspirated material from beneath the glottis PMID: 17766627). It is recommended that institutions adopt policies stating that routine suctioning for meconium-stained fluid and before the birth of the shoulders is unnecessary, as this stimulates the newborn to inhale, which can lead to postpartum depression and/or newborn bradycardia. Meconium-stained fluid occurs because the fetus is already having trouble in the womb. And suctioning at the birth of the head will not prevent MAS. A vigorous newborn does not require suctioning, regardless of whether the fluid was clear or meconium-stained.
Traditional midwives still turn the baby upside down to help them spit out secretions.
3. Cutting the umbilical cord
I’ve already written about this in this post: Cutting the umbilical cord. To summarize and perhaps add a few things:
It wasn’t always the case that the cord was cut before the placenta was delivered. Before the introduction of general anesthesia in 1900, the cord was cut after the birth of the placenta, unless the baby was premature. Different cultures have different customs, but they all share the belief that the cord shouldn’t be cut while it’s still pulsing. Ancestors believed the baby “breathed” through the cord and that it stopped pulsing once the baby was capable of independent breathing. Once the cord stops pulsing, it can be safely cut. In some cultures today, you’ll still encounter “lotus birth,” where the cord and placenta remain attached to the newborn for several days until the cord falls off on its own.

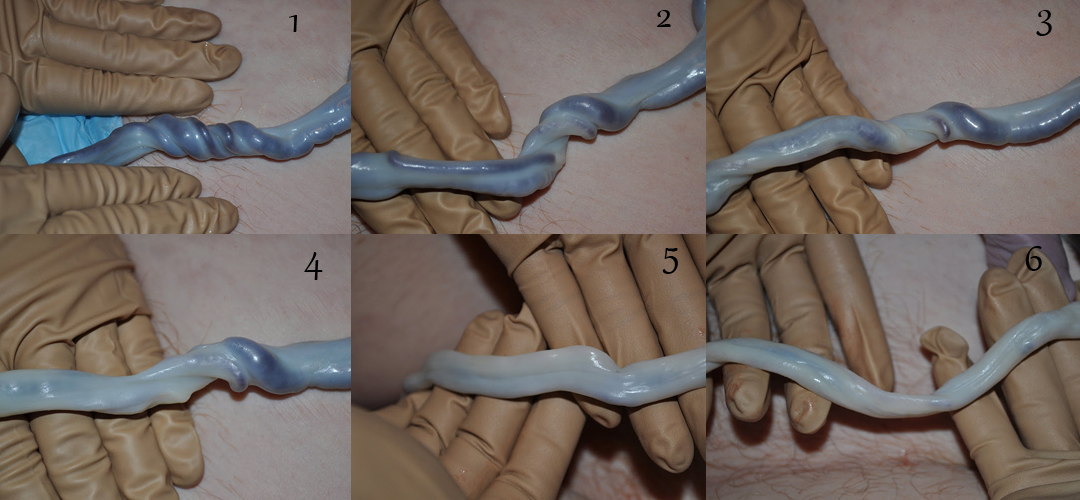
So, what should the cord look like before we cut it? White, empty, and not pulsing. When you can see with your own eyes that it’s no longer performing its function.

Why does the author “blame” anesthesia for the early cutting of the cord? When doctors started using gas for anesthesia, they were only just beginning to learn about the side effects it had on the mother (e.g., bleeding and liver damage). An obvious side effect was also that newborns had trouble breathing after birth. They had a good heart rate but poor breathing. So they had to take measures like suctioning and assisted ventilation. The routine back then was to turn the baby upside down and smack them so they would spit out secretions. To ensure the baby no longer received anesthesia through the cord, the solution was to cut the cord as soon as possible. This remains routine in some places today, even though anesthesia and analgesic therapy have advanced significantly.
Doctors were concerned about the introduced routine, but they knew it was the only way to save the baby’s life and mitigate the impact of anesthetics.